The Brown-Bag Audit at Home: A 20-Minute Medication Review for the Week After Discharge

Photo: Nancy Pelosi from San Francisco, CA, CC BY 2.0, via Wikimedia Commons
A hospital discharge can feel like a finish line, but medication safety often becomes more fragile in the days that follow. The patient leaves with new prescriptions, revised doses, and instructions to stop certain drugs. At home, those directions meet an existing cabinet of bottles, over-the-counter products, and supplements. The result is a familiar hazard: old and new instructions coexisting in the same space.
A brown-bag review is a structured way to reduce that hazard. The ritual takes about twenty minutes, requires no special equipment, and can be repeated after any major care transition. The goal is not to second-guess the hospital team. It is to reconcile what the patient is actually taking with what the current prescribers believe the patient is taking.
Step One: Gather Everything, Not Just the Prescriptions
Place every medication container in a single bag: prescription bottles, over-the-counter pain relievers, cold and allergy products, sleep aids, vitamins, herbal supplements, topical creams, inhalers, eye drops, and any leftover antibiotics. Include samples given at discharge and medications used only as needed. Add the discharge paperwork, the hospital medication list, and the most recent list from the primary care office.
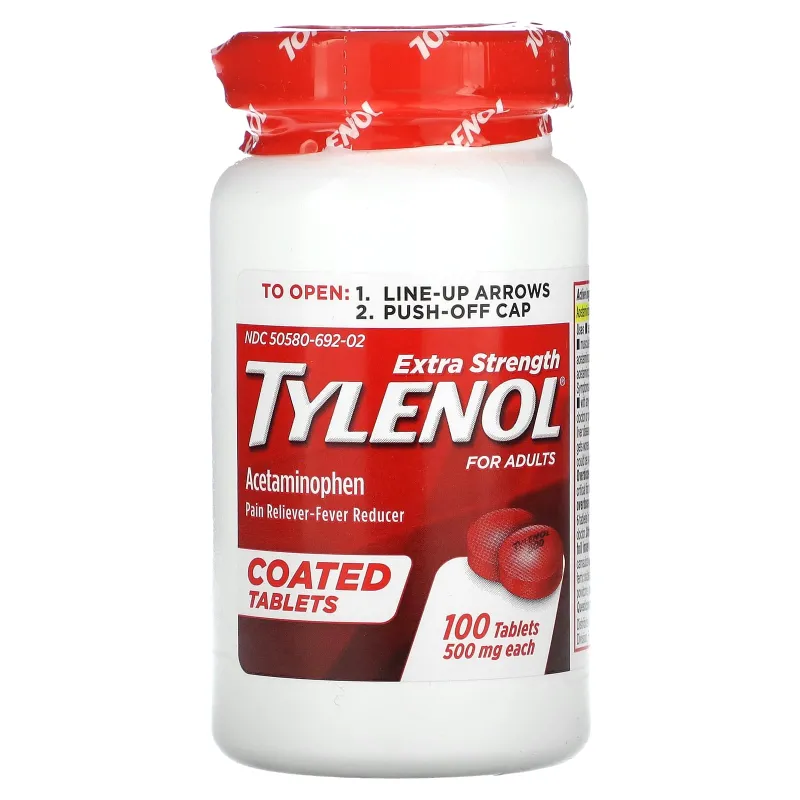
A complete inventory is essential because duplicates often hide outside the prescription bottle. A patient may be prescribed a sedative at discharge while continuing an over-the-counter sleep aid. A pain regimen may include an opioid combination product and a separate acetaminophen product. Neither overlap is visible if the review covers only prescription labels.
Step Two: Set Up a Clear Comparison
Choose a well-lit table and empty the bag. Separate containers into three groups: medicines the patient is currently taking, medicines that have been stopped or expired, and medicines that are uncertain. Keep the discharge instructions open. A caregiver or family member can read labels aloud while the patient confirms what is actually being taken.
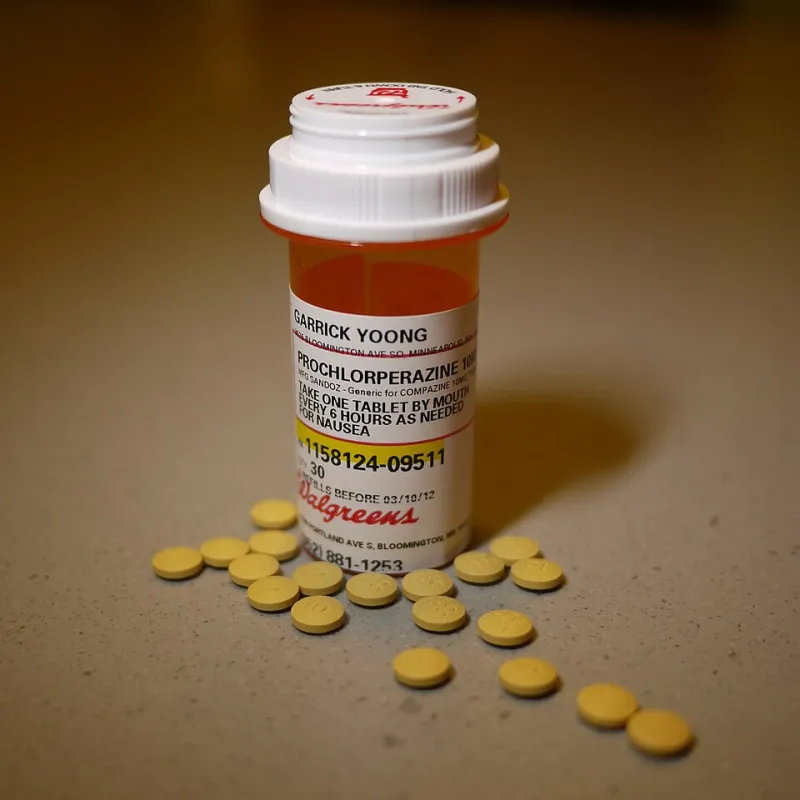
Do not rely on memory alone. The central question is simple: for every bottle, what is the drug, the strength, the dose, the timing, and the reason it was prescribed? If any of those answers is missing, the item belongs in the uncertain group.
Step Three: Look for Duplicates and Dangerous Overlaps
Duplicate therapy is not limited to two bottles with the same drug name. It also includes two products with the same active ingredient under different brand names, two medicines from the same class, and combinations that increase sedation or bleeding risk. Common examples include two nonsteroidal anti-inflammatory drugs, an opioid combined with a benzodiazepine, and multiple products containing acetaminophen.
Red flags include:
- Two bottles with the same active ingredient but different brand names
- A new prescription for a drug the patient is already taking under another name
- A stopped medication still sitting in the active supply
- Instructions that conflict between the discharge paperwork and the bottle label
- A dose that changed without a clear explanation
- An over-the-counter product that duplicates a prescription ingredient
- A supplement that may interact with a blood thinner or another prescription
Any of these findings warrants a call to the pharmacist or prescriber. The patient should not independently stop, start, or adjust a medicine based on a home review.
Step Four: Ask the Pharmacist These Questions
A pharmacist can reconcile the list efficiently when the patient brings the bag and the discharge paperwork. Useful questions include:
- Is this medicine still appropriate after the hospital stay?
- Does any new prescription duplicate an older one or an over-the-counter product?
- Is the dose on the bottle consistent with the discharge instructions?
- Are there interactions between the prescriptions, supplements, or alcohol?
- What should happen if a dose is missed?
- Which side effects require a call and which are expected?
- How long should this medicine be taken?
- Can any medicines be taken together, or do they need spacing?
- Is a different formulation available if swallowing or splitting is difficult?
- How should discontinued medicines be disposed of safely?
Step Five: Create One Master List
After the review, create a single current medication list. Include the drug name, strength, dose, timing, purpose, prescriber, and start date. Mark discontinued drugs clearly and remove them from the active supply. Keep the list in one consistent place and give a copy to a caregiver, the primary care office, and any specialist involved in care.
A pill organizer can support adherence, but it should be filled only after the list has been reconciled. Otherwise, an old dose can be carried forward into the new week. If the patient uses a pharmacy app or patient portal, update the medication list there as well.
Know When to Seek Urgent Help
A medication review is not a substitute for clinical care. Seek urgent medical attention for confusion, excessive drowsiness, difficulty breathing, fainting, uncontrolled bleeding, repeated vomiting, or signs of an allergic reaction such as facial swelling or rash. If a patient has taken too much of a medicine or the wrong medicine, call Poison Control or emergency services immediately.
The brown-bag review is a modest ritual with a serious purpose. It turns a cabinet of disconnected bottles into a verifiable record. For patients leaving the hospital, that twenty-minute pause can be the difference between a safe transition and a preventable crisis.